Tuesday, January 8, 2013

A Fragile Society


Stochastics... the end of reality and maybe the beginning of the end.

Read on...

The human element as some evolved intellectuals refer to themselves is composed of a fair number of basic elements, with Oxygen (65%) being the most common of all. Carbon, the basic unit of all organic molecules comes in at distant second place. Since the cells are composed of 65-90% of water weight, it is no wonder that Oxygen is the most prodigious element within the human element. Aside from Oxygen, Carbon (18%), Hydrogen (10%), Nitrogen (3%), Calcium (1.5%) and Phosphorus (1.0%) round out 99% of the total element base. Most of the remaining 1% is composed of, Potassium (0.35%), Sulfur (0.25%), Sodium (0.15%), Magnesium (0.05%) and other traces of Copper, Zinc, Selenium, Molybdenum, Fluorine, Chlorine, Iodine, Manganese, Cobalt, Iron (0.70%)Lithium, Strontium, Aluminum, Silicon, Lead, Vanadium, Arsenic, Bromine (trace amounts) – The elements of “Star-Dust.”


Why would I spend regurgitating such a litany of chemical names to bore you? Well consider the domain of the human element itself. It is this, a rather fluid and almost ripe medium for an external invasion, wouldn’t you think? I mean, seriously grasp the basic tenet of this argument by the neck and you can see that the ebb and flow of other microbial life can easily find “the rivers of plenty” in the human body to float in, proliferate, cohabitate and prosper, even to the detriment of the host.


The eco-system that some espouse, via agencies such as EPA to prevent and preserve the environment, fail to conceive of the environment within their own human element! But finding fault in others is the incomprehensible, but state of the art, schoolyard gambit of the elite. It maybe time for them to contemplate on their own navels. You see just like "tampering with nature" by exterminating one species ends up with unintended consequences. Reducing or eliminating minor stressors in daily life will lead to future tumult. 


We are a society, given to the excess of thought (sometime useless) like everything around us, we wish everything to be in a smooth and orderly fashion. There should be no rip-roaring ragged cliffs or deeply gashed valleys, just the smoothened road like Route 80 from Coast to Coast. But therein in the stochastic of our existence, we have also invoked and unveiled the most terrible of all curses. We have brought to bear the concept of sterility in all things, big and small. We have turned ourselves into the “bubble-populace!”

The human element is an evolving piece of ingenious machinery, conceived and crafted by the Great Tinkerer. By Creating the largesse of an “eco-system” of life from where to gather and learn from each other, becomes the single opportunistic directive for this human species that has managed to forge an intellectual bent some 2.5 million years ago (The dent in the left temporal region and the frontal region of the skull: where language, speech and decision-making lie).


Anyway, here we are floundering at the ragged self-replicating Mandelbrot’s .......



......coastline of disorder creating more chaos. We fail to see the ordered intelligence within the fractal coastline. We are busy bringing mounds of sand to smooth the coastline, knowing full well in the back of our minds that eventually there will be price to pay, through the ravages of a tsunami or an earthquake. We fail to heed that nature makes its own tracks.


A Mandelbrot Fractal


Think, how the species has evolved? Somewhere a long time ago, a unicellular organism (archaea) ingested a plant life (mitochondrium) and together they forged the self-organized, energy-independent cellular system that was to become the basis of all life form.


Now let us think some more about this incorporation of another life for a second.

The presence of Junk DNA in different species


Dwelling just a little on the DNA itself. There are Introns and Exons present in the helix of our life. Majority of the DNA used to be called “Junk DNA” because of our limits of understanding. 


Now comes the world-view that indeed here lie the species transforming gateways delivered onto us humans via the microbial life itself. Resplendent in their invisible but very able selves are the very essence of making life the fittest for survival.

Rut Roh!

Junk DNA may also be the very reason that life evolved as it did. Humans have the largest component of Junk DNA compared to all other forms of life


Translating Invasion through Invasion


What?

Oh yes! Indeed. Our exposure to microbial life is conducive for survival for both species. The microbes, be it viruses, bacteria, fungi, all serve a purpose in propagating and strengthening the future of life and by extension humanity.

I show this to show that exposure to constant radiation to certain form of bacterium resulted in the Radioduran Duran bacteria that is Resistant to high doses of radiation!


How?

Well, think about this little paradigm quietly. How many “bubble babies” can survive this harsh climate where microbes make our population look puny in numbers and abilities? The constant tug of invasion by the microbes, cohabitation within the human body, purge of the weak and Immune tolerance by the adaptive is the hallmark of survival. Isn’t that true?


Now, proceed with me into out modern current-day culture, where the definition of survival is based on how many “Purell Containers” line the hallways. What have we here? The modern day version of the “Bubble babies.”

True washing hands is a way to avoid getting infected, but to the point of fanaticism is beyond common intelligence. Some would snark and bark right about now. If washing hands is good, using Purell is better! Ah but something is lost on these souls. Washing hands is a prerequisite before attempting to eat a meal or where exposure to unsavory environment has been undertaken, but using Purell at every bend in the hallway is tantamount to eliminating the very elements that makes us resilient humans and gives us the wherewithal to survive. We are in essence trying to make our bodies so clean that they will not possess the ability to fight an errant germ.


Why?

There is a process called Hormesis. In this process is the small amounts of “bad” or “harmful” substances, both organic and inorganic constitute a certain strengthening of our  “exposed” flesh immunity. 

The purpose behind Hormesis is the small harmful elements exposure over time lead to Desensitization

A simile would be the desensitization to an allergen in a person who has allergies to a particular food or environmental product. The process of desensitization is the small but periodic irreverence of this exposure, which ultimately leads to acceptance and tolerance by the immune system for one’s survival.


Does the Flu virus mutate? Why of course it does, every season or even intrseason. We humans have the crafty science of mathematical modeling that determines which strain is most likely to strike and through that we predict the make of the Infuenza Vaccine (we are proven wrong more often then not). Even with the correct recipe, only 60% of the healthy and 48% of the sick are protected by the vaccination (CDC/NIH). It so happens that the crafty viruses are more adept at mutation due to their proliferating abilities. You see, a human generation changes every 15 years or so, while the viral generations grow at the speed of light; doubling of a virus takes minutes and thus is more adaptable to the environment via mutation, then the slow plod of human destiny. Here lies the wrath from the Influenza of 1918 where 500 million people were infected and 20-50 million died, the “Black Death” in 1848-1850 circa Europe that killed between 75-100 million people. Both had the commonness of an unprepared (immunity-wise) population to the ravages of a new pathogen, a lack of understanding, a virus in the former and Yersinia Pesitis in the latter.



Even in slow plodders amongst bacterial agents, mutation is the likely transformation that has created the pharmaceutical industry. Every generation of antibiotics is limited in functional time, because the bacteria mutate and acquire abilities to conform and survive the antibiotic attacks. There are a plethora of bacteria that have shown those capability; MRSA, TB, VRE, C-Diff etc. We are constantly trying to “kill” the “un-killable.” In so doing, we are creating bigger monsters. Equally, viruses have the same capabilities; Hepatitis B virus which has transformed from HBV-A to HBV-I with multiple layers within each subdivision is a product of selection bias of the HBV exposed to various vaccines, Hepatitis C virus with its four subdivisions and of course who can forget HIV.


But aren’t the viruses bad all the time?


Not really. You see our DNA as I mentioned is made up of many viral particles that reside within our DNA as inclusions (junk). These viral DNAs portions can come to reside next to genes that are in the business of proliferation. The viral inclusions can thus act either as “Inhibitors” or “Promoters” of that gene function. If that gene is triggered in a cancer the adjacent viral DNA if it exists, can enhance either of those duties, which can either shut down the gene and prevent cancer or enhance the gene and make the cancer become more aggressive. The c-myc, n-myc, ras and scores of other genes all conform to these ideologies. Read further here~> http://phys.org/news114266805.html

Economics 101

Our thinking of mitigating risks has reached a new climax, which is also inherent to our precepts of “sterility.” The use of Purell in every hallway is like “bailing out a company in distress.” Using an orderly bankruptcy due to the limited exposure to self if not allowed in a rational and systematic manner of enhancing the immune surveillance and survival, will lead to a large “Failure” of the entire body later.


Giving everyone a house with a picket fence with “cheap and easy” money that the top-down politicians deemed a winning strategy for re-elections, lead to the financial debacle of 2008. The sense of bundling mortgages into traunches (CDS, CDO, CLO,MBS) was an attempt by the mortgagors to limit their own exposure by spreading the risks to the many. And that “Risk” became the calamity that is today. But the intellectuals at the seat of government remain ignorant based on their ongoing behaviors and foster a newer version of the failed mandate. Oh but for the profligate idiocy in humanity!


Will the human species survive? Maybe to a yes. (As long as we don't destroy ourselves)


It is the miracle of the "Jumping Genes" or the Transposons that have helped in finding the answers for the evolving human race (See http://jedismedicine.blogspot.com/2011/02/human-diversity-in-genes.html?spref=tw )

I would be classified as a nihilist by many waiting to pounce on the above words. For if anyone dares to express an opinion differing from the "experts," then he or she must be reclassified through the artistry of demonizing.

So what have we wrought?

A panacea against disease?

A plague for the future?

Or just “kick the can down the road” towards a colossal calamity?

You decide.

I'll pay that doctrine, or else die in debt. ~ Romeo and Juliet, Shakespeare

Thursday, January 3, 2013

KIDNAPPING MEDICINE


"When sages commend excess, desire is sick!"
I came across an erudite article from a very polished source the other day. His premise was that too much information could expose physicians to a higher chance of malpractice litigation risk. (Dr. Wes Fisher is an interventional cardiologist and blogs at “Dr. Wes”)

So I asked the question, why would more information enhance such a risk? Why indeed?

His arguments in the article, here http://www.kevinmd.com/blog/2013/01/information-overload-doctors-increases-malpractice-risk.html are well balanced and true. He argues from the perspective of the Electronic Medical Records where “Clicking” and accepting someone else’s (a nurse, NP, PA, another physician’s and even the hospital’s) statements/recommendations get “auto-ordered,” much like the “pneumovax vaccine assuring the hospital excellent public reporting metrics.” He argues that given the time constraints in a “multidirectional electronic communication” medical environment and the “avalanche of items,” the doctor has to spend extraordinary amount of time, completing the medical record and in haste or another competing medical emergency, may click and accept responsibility of another’s action, that might expose him to liability. All that is self evident and true because the legal eagles love the retrospective review.

In the medical world where minutes are measured in hours and hours in days, compacting the flow of information and action in a non-discriminatory digital throughput has the physician on the wrong side of the microscope.

So what of this?

To further delve into this information overload conundrum, I turned to aviation. Why aviation, you might ask? Well if you have been following the quasi-medical chronicles by the medical and non-medical sages of today, there is an emotionally satisfying appeal in equating pilots to doctors. Some less informed but clever writers, even state bluntly, “If pilots worked like doctors, the sky would rain planes” can be found here: http://www.kevinmd.com/blog/2012/11/pilots-worked-doctors-sky-rain-planes.html

The view from those eyes, fails to take into consideration a lot of issues inherent in medicine and for that matter in aviation skills. The skill set and knowledge base are fundamentally different as is the format of knowledge acquisition and the required training.  

Even though certain correlations do exist as they would in any scientific, engineering, electronic or mechanical discipline, where an epistemological rigor is present, but not the kind being bandied about recently. Human lives are at stake in medicine when disease manifests, unlike in aviation or for that matter in driving a bus or even a car, where mechanical standards apply. The desire to integrate such disparate disciplines harbors within the lack of real knowledge about the multiple co-morbid states in human beings. A mechanical aircraft cannot equate to the lub-dub of the beating human heart. A person undergoing surgery for a gall bladder may have issues related to stress-hyperglycemia, which might expose him or her to a higher risk of infection, a minimally weak heart that might go into heart failure from the surgical intervention, a weakened immunity from a undiagnosed viral agent, anesthetic stress or an allergic reaction to an anesthetic agent. These are contributing factors to unquantifiable risks that before hand cannot be mitigated a 100% (much as "experts" would claim they can and we should). Once the hazards are determined, the events are addressed by the physicians and mitigated accordingly. One can only be cognizant and alert to known hazards. Additionally, help is always nearby. In difficult medical cases, where other physicians are called in to impart their expertise and provide help.

In driving a car the driver is ignorant of a loose brake-pedal screw (unless he checks for it before each drive), a faulty torque tube or an electronic sensor that sends imperfect fuel information signals (slapping and kicking may cause it to flicker the right signal only some of the times). Unless the driver examines the car with X-Rays for every fatigued metal before each use, malfunctions can and do occur anytime with failures, leading to accidents. The driver’s skills might save the day in some circumstance but not all. And thus a roadside calamity would not be for the lack of experience, but chance. It is true that there is a 0.43 risk of fatality per 100,000 hours of flying while the risk in driving is 20.3 risk of death per 100,000 hours of driving, one cannot equate these events to those in medicine. Where the two have in common is the surplus of unwarranted information that can color the circumstance and prove hazardous. Where they diverge, well... Medicine like all others, is not a perfect science, but this provocative unorthodoxy of combining disparate disciplines of aviation recurrent training and medical re-certification to reduce risks is without merit and is done mostly to reap personal gains and polish a vanity that is in search of a mirror.

Let me explain further.

In aviation, the pilot peruses the checklist before each flight (A similar “time-out” is now an accepted format prior to surgery to prevent errant intervention). You might have seen the pilot walk around a Boeing or an Airbus; you are seated in, looking at the wings and the gear as he eyeballs information during his walk around. A similar evaluation is accomplished by the surgeon before surgery. He then spends several minutes in the cockpit reviewing his checklist. Even then there are circumstances of fuel contamination, metal fatigue, autopilot failure due to a faulty resistor, electrical fire due to shorting, loss of hydraulics, engine flameout, gear retraction or extension failure and a whole host of things that can cut a flight short. The pilot and his/her co-pilot address these issues during such a malfunction, additional help can be had for the pilot, from the Air Traffic Control by patching his call to his company’s service center with issues that may not be detailed in the Pilot Operating handbook (POH).

In medicine most physicians review new information about complicated cases and are adept at regaling themselves with the newer fund of knowledge to better care for their patients. After all, a requirement of 50 hours Continuing Medical Education is a prerequisite for maintenance of license to practice across the United States! Whereas in aviation it is the eye-hand coordination in flight review and responses to simulated emergencies, in medicine a re-certification examination is a learning by rote of esoteric conditions that one rarely encounters. Speaking of conditions, I have as yet to see a case of "Acinic Cell Carcinoma" that had a total of 5 questions in the last re-certifying board examination in Medical Oncology. If I was confronted with such a diagnosis, there is plenty of literature to educate me. Having answered those questions correctly, I do not recall the answers today, since the "rut" in brain is formed by the daily adventures. The kind of information requested in these Certification examination is mostly unusable trivia that takes hours of study with no benefit to the patient. 

While medicine deals with the anatomy, physiology and pathology of another human, aviation is a human determining the functionality of a mechanical airplane, thus medicine is not and cannot be reduced to a context-independent, deterministic set of mathematical terms. This disputatious relationship that many are eager to combine in their theoretical soup, fails to undergo the rigors of reason. Ilya Prigogine’s “End of Certainty” suggested that the human rationale exists in the spectrum from “Becoming to Being” through the acts of reason. Unfortunately reason is the least common denominator in the current day of “being!” We marvel at a process and then try to merge diverse and opposing concepts under the conceit of intellectual bias. After all John Dryden’s “noble savage” that later became Rousseau’s “natural man” was gifted with an innate goodness that with “reason” transformed society into the “Social Contract” for humanity's civil existence. The Social Contract was not one designed by the selfish desires of self-aggrandizement. But by logic, reason and intuit.

However much we are enamored by the glitz and glamour of aviation safety, there exist significant problems in this glorified discipline also, even though they might be hidden from the non-discerning eyes that proclaim its grand vision. For instance, getting back to the original premise, information overload is one of them. Too much information is a calamity for both physicians and for pilots. Unnecessary data fed to pilots confuses the mind. (The taoists wisely suggest that one cannot fill a glass that is already full). During an emergency, a pilot is trained to feed his brain with the following: “Aviate, Navigate and Communicate” in that order. In the aviate portion, a pilot has to discern the flaw that has culminated in the system malfunction and try to eliminate it and if not, then find alternate methods to circumvent the occurrence. Early recognition leads to early elimination and possible prevention of a catastrophe. Early recognition comes from experience and knowledge. Only after the “aviate” portion has been accomplished, that is to say the plane is not allowed to depart the flight envelope, should the pilot “navigate” and consider looking for a place to land and once that is accomplished then “Communicate” with the Air Traffic Controller, declare an emergency and seek additional help, if needed. These three words have saved countless lives! A simplified directive!

Too much information at the wrong phase of flight can lead to disaster. On takeoff or in the landing phase for instance distractions can have bad consequences. The current Glass Cockpit displays reveal reams of information on a single screen for the pilot and have lead to compromised safety.

“The US National Transportation Safety Board (NTSB) sent out a press release yesterday (2010) saying that it had "adopted a study concluding that single engine airplanes equipped with glass cockpits had no better overall safety record than airplanes with conventional instrumentation." http://spectrum.ieee.org/riskfactor/aerospace/aviation/ntsb-study-shows-that-introducing-of-glass-cockpits-in-general-aviation-doesnt-lead-to-expected-safety-improvements
“The study, which looked at the accident rates of over 8,000 small piston-powered airplanes manufactured between 2002 and 2006, found that those equipped with glass cockpits had a higher fatal accident rate then similar aircraft with conventional instruments.”

It is in the essence of the needed information vs. a plethora of meaningless data, where safety exists, both in medicine and in aviation. It is and would be a meaningless, albeit a wonderful newsworthy splash, by equating aviators with physicians in outcome studies.

Consider this: Pilots undergo recurrent training to verify their abilities in understanding and mitigating emergency situations. They learn about what happens if the aircraft loses hydraulics, or electrical failure, or engine flameouts or avionics malfunction? It is hands on manipulation of the controls in the simulators in aviation training. The pilots have to review and understand their pilot operating handbooks (POH) "specific for each type of aircraft" during the recurrent training and have hands-on experience in the comfort of a simulator where crashes have no consequences but a bruised ego. There are no punitive pass/fail, just time and more time in the simulator. This sharpens their skills in case of an emergency during actual flights. Physicians do the same with daily experience, CMEs and annual seminars and meetings and to boot they have to be cognizant of the many ailments of each organ!


Speaking of critical thinking of a superior mind: the critical thought of Sullenberger in ditching the US Airways flight in the Hudson River was not taught at any recurrent training scenario but as a result of his experience and good decision-making skills. Logic would have made him turn back to LaGuardia Airport or try for Teterboro Airport both within sight, but his sharp skills realized the risks were much greater with loss of vertical component of lift in a turn back for the former and the risk of harm to the populated terrain below in the latter trajectory ~ both might have resulted in loss of life.


Similarly preventing the loss of 185 lives in the United 232  Sioux City Iowa crash in 1989 was the “out of the box” thinking by Captain Al Haynes and not because of any training scenarios in the simulator. He used vectored use of the remaining two engines to control direction of flight and altitude without control surfaces to reach Sioux City. In fact 55 test pilots attempted to do in a simulator what he did in reality given the same circumstances and failed with 100% catastrophe. 55 test pilots!

http://youtu.be/WLiqJa-wSFk


Meanwhile, the 1977 Tenerife Disaster was blamed on the arrogance of Captain Jacob Veldhuyzen van Zanten of KLM flight 4805 and the Pan Am flight 1736, both aircraft were Boeing 747. The problem here was the Chief Pilot Van Zanten, who had his face on the cover of Time Magazine, as the best-trained pilot who gave fight training and he became the object of arrogance and disobedience of flight rules. 583 people perished as a result. So not all beauty lies in this comparison.

http://youtu.be/sNZOOw69L0k


Even though Dr. Wes and others have written about the shadows that linger over medicine with a certain precautionary veil guarding their sentiments, there needs to be an intellectual debate over the plagued blackness that some enshroud the field of medicine. Besides too much information, the wrong kind is being deemed expositive by academic physicians who have long since been out of practice of medicine.

Here, Dr. Wes does not mince any words, “The Punitive Evolution of Board Certification” http://drwes.blogspot.com/2012/12/the-punative-evolution-of-board.html


The latest salvo against physicians comes from the American Board of Medical Specialties (ABMS) that advocates the need for continuing Maintenance of Certification. Their surrogates use the aviation pretext and state that pilots need recurrent training every six months to maintain their abilities, why not the doctors. these surrogates citing that the six monthly recurrent aviation training leads to safety in aviation, the ABMS wishes to establish a biannual examination to maintain certification, which then can later be tied to maintenance of the license of a physician to practice medicine. This is an unfortunate series of unwarranted comparisons made for financial self-enrichment and self-aggrandizement. While there is no doubt that a pilot loses his or her proficiency when not flying frequently, just like a video game aficionado, it is recommended an airline pilot should undergo six-monthly recurrent training at the designated company’s test centers and a general aviation pilot have a biannual flight review (since the general aviation pilots do not fly for a living) by a certified flight instructor (CFI), equating these recommendations for pilots to that of physicians is equating “apples to oranges.” A surgeon for instance operates almost daily while not so for a pilot. In piloting, it is decision-making and “eye-hand-coordination,” mostly. In medical practice it is not! Surgeons by their very experience and various courses become experts in their expertise and maintain this rigor throughout their careers. Family physicians through current experience and knowledge and their annual CMEs reap the same harvest for their patients. Further adding to the burden on a physician with illogic and lack of evidence based esoteric knowledge, is tantamount to eroding the skills, critical thinking and rational decision-making. Besides as mentioned before, unrelated esoteric information cripples good decision-making.

How many surgeons, pediatricians, family physicians, oncologists, orthopedists and other specialties have saved millions if not billions of lives over the course of human history. One will never know. But most never see the good in anything.

It all comes down to the proper form and amount of information needed to process in any circumstance. And within the rigors of that processing lies the golden rule of “Reason!” The esoteric reveled by the ABMS in their MOC does not save lives, nor does it help improve patient care (All data supports this statement). Delivering excess information through electronic or any means disrupts good patient care and as evidenced by the FAA study mentioned above, good piloting. The implied and forced epistemological rote leveled at the layperson via the uninformed media creates the nuance of “Scientific Rigor,” where none exists! The kidnapping of good medical care continues...

It all boils down to the right information at the right time… And REASON. 

The current art of reductionism will soon have doctors being compared to dish washers and many will pipe in that it is the water, or the spray or the speed of the water flow that needs to be addressed to fix medical care. ~ Reductio Ad Absurdum!!!

Let me leave you with a thought expressed by  Mason Cooley:

"When sages commend excess, desire is sick!" 

Monday, December 31, 2012

Happy New Year


I opened the door today and there in front was a package. It is after Christmas and today is New year’s Eve to boot. But there it was tied up nicely in a red bow.


It felt light, very light.

I opened the package.

And there was a letter in it.

“Dear JediPD (I know, you know that I know who you are, so we will leave it at that),

Rudolph had a routing by your house, so I asked him to drop this off.”

“Rudolph was here!” I exclaimed, loud enough to catch my own words in mid sentence and lower the pitch and loudness for fear neighbors might raise their collective eyebrows.

The note goes on:

“I have noticed an edge in your words and gently suggest you tweak them, I know in your heart of heart there is a well of good wishes for everyone. So let them show, but not with an edge.”

Had I been so overtly insensitive? Maybe? But then again I thought I was just stating the obvious as it appeared to me. Edge? What edge? Go on…

“Remember it is the good deed and not the spoken word that ultimately survives.”

You can say it again.

“But words hurt.”

Yeah but, sometime one needs to express the obvious, you know!

“I know you feel that you have to express the obvious, but try it delicately.”

Boy can he read my mind!

“So here is the essence of what I am saying.”

Do go on…

“Work hard at what makes you happiest, make others happier, educate them of what knowledge you possess and learn from them what they know.”

Uh huh…

“It is in the mind meld of many ideas that a true thought is born that can change the world. And I agree, this world needs a little help.”

Does it?

“And if you do this well, next year expect a real bonus for your hard work from me. I am expanding my sleigh volume for just such bonuses for many like you. (Plus Rudolph has been building his muscles and his nose now shines like the light on the Polar Express locomotive. Oops, I forgot you don’t have locomotives anymore, do you? It’s the Mag-Lev or some stuff like that.”

We have space shuttles, solid fuels and high bypass turbines baby! No need to worry about cracking the frozen ice on a lake anymore.

“Anyway, think about what I have said. Work hard and the bonuses will come.”

And what would the bonus be?

"The bonus will be something that your heart will desire then, not now. As you know time changes everything!"

Whoa how did he know that? Creepy.

“But if you sit on the sofa all day, playing with the iPad or the video games on your computer, then, I am afraid, your home address might be struck off Rudolph’s roster. But that you already know.”

Pray tell that to others too…while I shut down this computer.

“Anyway, wishing you and your family a Happy Healthy 2013 and beyond and hoping that I can fill your bag of goodies to the hilt commensurate with your hard work.”

Signed:


Santa Claus
2012


Saturday, December 29, 2012

SGR and Physicians


The beast within grows. Its white fangs and long curled talons seem like a caricature in a sci-fi movie, than real life. But there it is, the Gryphon, baring its teeth encrusted beak and its hawkish eyes under the brown and white ruffled feathers that spell dominance. The creature is restless, as its deep-dark eyes dart from side to side.


The SGR seems oddly to fit the image of this beast. Born of a thought for containment, as a dovish sort of benevolent bird, flitting about from tree to tree, it has eaten off the forbidden fruit of procrastination and turned into this giant beast of hawk-like demeanor with a reptilian cold-blooded calculating mind-set.

What is SGR (Sustained Growth Rate) formula after all?

The Medicare Sustainable Growth Rate (SGR) is currently used by the CMS Centers for Medicare and Medicaid Services in the United States to control spending by Medicare on physician services. The SGR was enacted by the Balanced Budget Act of 1997 to amend Section 1848(f) of the Social Security Act and replaced the Medicare Volume Performance Standard (MVPS). CMS previously used MVPS in an attempt to control costs. Generally, this is a method to ensure that the yearly increase in the expense per Medicare beneficiary does not exceed the growth in GDP.


“Every year, the CMS sends a report to the Medicare Payment Advisory Commission, which advises the US Congress on the previous year's total expenditures and the target expenditures. The report also includes a conversion factor that will change the payments for physician services for the next year in order to match the target SGR. If the expenditures for the previous year exceeded the target expenditures, then the conversion factor will decrease payments for the next year. If the expenditures were less than expected, the conversion factor would increase the payments to physicians for the next year.”

The four factors involved in these calculations include:

               1. The estimated percentage change in fees for physicians’ services.
               2. The estimated percentage change in the average number of Medicare fee-for-service beneficiaries.
               3. The estimated 10-year average annual percentage change in real GDP per capita.
               4. The estimated percentage change in expenditures due to changes in law or regulations.

As one can guess, given this oddly figured attempt to control healthcare costs, the physicians are being used as the “sacrificial lambs.” While on one side there is a “push” to invest in conforming to regulatory requirements and added jungle of complexity, which any kindergarten student will tell you, adds to the costs of care, the other side is hell-bent on “you can’t raise prices!”  The only thing close to reality would be telling McDonald Restaurants to have seating for hundred customers in each restaurant and hire 20 extra employees to service the stations and oh but you (McDonald) cannot raise the prices of hamburgers. Hmm…


And here is a real world personal example: When I first started practicing medicine, I had one employee. She was the front-office and did everything else except practice medicine. Then as time expanded and as needs grew, my office expanded the workforce to two and then three and before, I had a chance to realize it, I had 10 workers staffing a one-physician facility. There was a billing person, a coder, an insurance pre-qualifier, two nurses, a chart filer, a front office receptionist, an office manager and two laboratory technicians. Not to mention other contractors for computer services, OSHA regulatory compliance, COLA and CLIA regulatory compliances. So all in all, keeping this large workforce to continue providing healthcare services required a larger revenue stream. The SGR creators on the other hand remained distant and oblivious to the external forces enacted by the congressional experts that were constantly shaping and adding the streams of burden on a physician’s abilities. The simple act of comprehension seemed oddly absent in the mix of these “experts.” The one hand continues to harvest “nothing” while the other hand continues to “seed” something; simultaneity of complex idiocy.

While the Congress and the Executive branches have been reviewing the burgeoning “big” data based on a falsified premise, and believing in it’s virtues they have nevertheless continued to “kick the can down the road.” Already in arrears for -27.4% over the past decade, there is very little “stomach” to stomach the potential “backlash” from the physician and patient advocacy groups. Both will lose a large number of care-givers and care-needy numbers. And if the new movement of rising numbers of “hospitalists” (physicians employed by the hospitals to render inpatient care) is a comfort to society, the SGR follows the physician wherever he goes and that brings the hospital revenues under scrutiny and potential pressure. The AHA lobbyist are already at it, spinning their intellectual wheels to find the cure for this contagion. And the beat goes on...

The vitriol continues about the “rich doctors” and their lifestyles of big houses  and expensive cars, as the clarion call to rally the masses in support of the impending cuts continues. Yet even this weary class-envy seems not to bring in the desired angst from the populace, for they fear a loss of “something” for themselves. The “warfare” against physicians continues while the public “servants” fly around under Rolls Royce powered jets from halls of congress to their districts and are wined and dined by corporate magnates to enforce the cuts so that larger portions of the insurance premiums become the incremental added share-value. Ah! But I digress!

So here we are delaying the inevitability based on the faulty premise to begin with. Yet this delay diverts the consequences from now to the future where the pain will be greater and survivability not insured. This persistent delay will rear its ugly head as a rampant inflation of a dislocated reality where healthcare will suffer at the alter of fewer physicians and many “compliance czars” that mete out the marginalized healthcare.


Ron Shinkman of Fierce Health Finance states,
“As a result, doctors are facing a 27.5 percent cut in payments for the care they provide--the accumulation of a decade of cost deficits that have never been addressed. It's a deeply ludicrous cut and will never happen, but it exists solely because of past inaction.
Meanwhile, as the Affordable Care Act takes greater hold in 2014 and the years after, there is likely going to be more pressure to keep the healthcare cost curve down. If Massachusetts, the ACA's original home, is any guide, inflation is going to move up from its current historical lows pretty quickly.
A variety of health policy experts have noted the SGR tug-of-war has kept the physician community from focusing on properly implementing reform.”


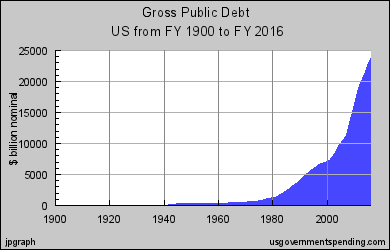
US Federal Debt ~ Projected


United States Public Debt


Let us briefly cast our view on the world of finance, it is akin to the “doc-fixes” that have been implemented over the past ten years. There is no appetite for risk. No appetite for new beginnings, just the same old “kick the can,” experience. The Non-risk takers have ensconced themselves and now lord over the risk-takers. “Nothing can be done that rattles any person,” is the rallying cry. The political correctness sting is on. And what this begets is a future that follows. Greece is a perfect example of this glorified pervasive European dysfunction that seems so desirous in the United States. Greece is only a “Nein!” away (no more free Euros from the working class) from devolving into anarchy and chaos, followed closely by Spain and then Italy. A US debt to the tune of $16, 337,000,000,000.00 where almost $950,000,000,000 are paid out as interest annually is 104% of the GDP (Gross Domestic Product). And should you desire to know, Greece is at 178.4%. Spain is at 90.4% and although that might be comforting to some, it is also wiser to know that Brazil and Mexico both defaulted with debts to GDP ratios of 50%.


The Greek Debt to GDP


Greece GDP


Getting back to the Mediscare called SGR formula, the essence of this ensuing debacle lies squarely on the inefficiencies of a bureaucracy that allows for exploitation by the bad elements in society, A payment formula based more on the “lobbyists-determinant” rather than the actual cost and a “ivory-tower” controlled by the non-risk-takers who manage the levers of control, compare and contrast.

Are there inefficiencies in healthcare? Yes!
Are there better methods of delivery of healthcare? Yes!
Are there efficiencies that can be exploited to benefit the system? Yes!

The one-word answers exist in the Risk-Taker realm but not in the exploiting bookish world of “experts.” Just like an economist (Nobel Laureate or not) who has never balanced a checkbook will never know the levers that govern the real world. The consequence of an action is never contemplated by these rarified few. An expert high up in this “high-up” world of  “do this…” has no concept of how medicine is really practiced or for that matter how the world really works or the costs that are incurred and what will be the rip-tide consequences of that "do this..." They just sit and profess…

Ignoring these precarious risks, with vacant eyes, of the beast that lurks is forbearance of what is to come.

Meanwhile the fangs and talons get bigger and bigger and the tail whips and whips hungrier and hungrier...


References:

SGR Formula
http://www.cms.gov/Medicare/Medicare-Fee-for-Service-Payment/SustainableGRatesConFact/index.html?redirect=/SustainableGRatesConFact/

Medicare Volume Performance Standard (MVPS)
http://www.cms.gov/Medicare/Medicare-Fee-for-Service-Payment/SustainableGRatesConFact/downloads/sgr2010f.pdf

Medicare beneficiary expense and the GDP
http://blogs.wsj.com/health/2008/07/10/why-medicare-pay-cuts-for-doctors-will-be-back/

SGR and the “Cliff” ~ Ron Shinkman
SGR faces its own fiscal cliff - FierceHealthFinance - Health Finance, Healthcare Finance http://www.fiercehealthfinance.com/story/sgr-faces-its-own-fiscal-cliff/2012-12-11#ixzz2GSwwKnpC

The Sovereign Debt Crisis: A modern Greek tragedy (Federal Reserve Bank of Saint Louis)
http://www.stlouisfed.org/publications/cb/articles/?id=2264

Sunday, December 23, 2012

T'was the Night Before Christmas


The Silence of the night
Has, many voices
The night before
Has, many days.


When the lab’s ears
Have flopped shut
And the cat’s
Meow is a purr
The dark landscape
Is a tumult~
Of houses and hills,
Of vacant roads
And snow-flakes in still.
Merry Christmas to all
All will be well!

When lights are dimmed
And life dreams
Of elves and sleighs
Of cookies and milk
A painful cry leaves
An ache in its wake
And the bleary eyes
Shake off the fog.
The need is great!


Beneath bright lights
The watchful eye
Governs the landscape,
Ache is identified
And the pain is released.
The eye discerns
as the ears monitor
and the brain weighs
All is well.
Merry Christmas
You will be well!


The doctor reaches
To leave and catch a wink
But the morning
Has broken.
More lives need a rescue,
More hearts need a mend
The Night is not yet done
Humanity still needs a link.
Merry Christmas to all
All will be well! 

Thursday, December 20, 2012

A Brief History of Medicine (1965-2012)


The Changed Paradigm

President Johnson signing the Medicare Act 1965


The United States transitioned from a 1000+ year-old model of fee for service to a third party payer model. In 1965, Congress created Medicare under Title XVIII of the Social Security Act to provide health insurance to people age 65 and older, regardless of income and younger people with disabilities. The purpose for this transition was to create a safety net for the retired individuals to have healthcare when their individual resources were fixed and no new source of revenue was available to them. It was a great boon for the elderly. The payment model was quite simple: after the physician interaction, a form was submitted to the CMS Medicare by the patient and within six weeks the money was processed and the patient paid directly. The public viewed it, massaged by the relentless media, as a transition from a horse drawn buggy to riding the Mercedes.


Medicare Assignments

Soon the polity decided that if the physicians participated in accepting assignments, they would be paid a small premium over the normal costs as a bonus and all payments would then be sent directly to the physicians. This had a two-fold advantage for both the patient and the physician. The patient did not have to outlay for the initial bill and the physician under most circumstances did not have to wait for the patient to be paid in order to receive his or her remunerations. The physicians lined up in droves and those that didn’t the market forces forced them into the fray eventually. After all the population was not getting any younger.

The time value of money was definitely on the government and the patient’s side since the six-week and sometimes more delay in payment due to processing delays, favored the two entities and not the physician who had already expended work and energy some time ago. Why quibble about minor things?

ICD codes and Denials

Lo and behold as things became complicated with the ICD coding promulgated by the Government and created by the AMA at a cost of millions to the taxpayers, to use as measurable metrics, the decisions regarding payment of legitimate expenses for rendered care resulted in an automatic 12% denial. This denial was willy-nilly and reasoned as poor interface of paper submission. If the physician office who was the direct recipient of the monies was not on top of perfect paper submissions with the right “ps” and “qs” a denial would be generated by the central (Medicare) and peripheral (Non-Medicare Insurers) planners. The interface between the patient and physician remained at the health level but the cost of that care was now directed towards the government and third party insurance. And if the physician’s office with its burgeoning staff, to accommodate the bureaucracy, was equally incompetent and limited in knowledge of processing the claims, then the physician suffered an economic blow that became apparent to him or her at the end of the year (since physicians by their very nature are not business people). Once the bulb of understanding was lit, it was already too late, further claims resubmission could not be processed because of the 90-day resubmission rule at the Insurer level. So the dragnet of financial squeeze was in place.

Electronic Submissions of Claims

Along came the digital age and every office had to now perforce of mandate employ the digital mode of claim transmission. Well as you might have guessed the initial processing was quicker with a 3-4 week return on the claim. Suddenly the denial rate increased many fold because of the missed “.” and “,” in the generated claims report. Additionally quasi rules of payments were conjured up based on soft “evidentiary” rule-making. This resulted in denials for “appropriateness of care.” The once reasoned arguments for reimbursements now became unreasonable. Given the electronic submission of data, an automatic audit was created to evaluate “appropriateness of care.” Never mind the complexity of the care given, if there were too many high-complexity claim submissions a report was generated to chastise the physician and ultimately used as a denial of services or better yet there was a demand for return of payments via automatic Audits.

As the utilization of the services increased, due in part to an aging populace and because of the multiple co-morbid states represented on the ICD coding method, the healthcare spending rose dramatically, climbing first to12% and then up to 17% of GDP in 2010. With one eye on payments and the other on the spiraling costs, the Insurance audits increased in frequency and more and more human resources were employed in the game of “I did!” against “you did not!”

Alarms and Bells of all shapes and sizes rang out loud and clear that this was an unsustainable progression of events and that something needed to be done to harness this wild and intemperate healthcare beast.

Medicaid, Municipalities, Bankruptcies and Employers.

The model promised and promulgated by the central planners was to provide Universal Healthcare but in conceiving of this largesse they failed to take into account the costs that would be incurred. The states already whimpering in their own financial straits were looking at their own fiscal cliffs of insolvencies and many decided they did not want to partake in the management of the ever-increasing Medicaid eligible individuals because it would collapse them into bankruptcy. A large gaping hole yawned ahead of this conceived healthcare agenda. Physicians, reeling from the non-payment and low-payment model of Medicaid reimbursement cancelled their participation in the Medicaid services, leaving several thousands of the low-income people under the Medicaid rolls without caregivers. (The cost of care delivery exceeded the reimbursements ~an untenable situation for private practitioners). This impact was felt at the state and municipality level who were left without money and a bloated bag of IOUs. However they paid themselves handsomely all the same.  In fact four municipalities in California alone declared bankruptcy due to unsustainable costs of rendering services and paying for their own heath benefits and those of its employees. The Universal Coverage model was fast becoming a forced reality with ultimately the Federal Government will end up undertaking the care of the Medicaid eligible individuals. (Not to mention the employers who shun healthcare subsidy for their employees and agree to pay $2000 fine to save $12000 in premium coverage for the same would result in a sea of uninsured individuals, filling the Medicaid rolls). The burgeoning rosters of people needing medical help and little available provisions of care for the same became a dilemma where something had to be done. The falconer was losing sight of the falcon.

IPAB, P4P and EBM.

The only route to control costs was rationing the expected care, Committees like IPAB and NCAB were established to figure out the appropriateness of care delivery. (This scenario has yet to play out). Not withstanding the demands of the elderly and the poor the scenario seems replete with cost curtailment by acronyms like P4P (pay for performance) and EBM (Evidence Based Medicine). The problems with eaxh of these, remains as to how does one consider performance? The P4P is already being played out, and as all such implied top-down simplicity faces the day of reckoning, the physicians realized that the really sick patients would reduce their (the physicians) performance numbers. So they stopped accepting complicated cases and referred them to the tertiary centers. In time the tertiary centers saw their “health grades” dip due to high costs and poor “performance” and that racked the ivory tower industry to the core. Suddenly articles populated the journals decrying that P4P doesn’t really work and a better system needs to be in place. What was good for the goose was not apparently good for the gander.

As far as the “Evidence Based Medicine” scenario is concerned, it was based on the shifting sands of the word, “Evidence.” In medicine, as in all fast changing fields, today’s evidence is tomorrows “What were we thinking?” that if latched on to, will exact its own pound of flesh.


EMRs.

The metrics for measurable intent was falling apart and along came the EMRs (Electronic Medical Records). The federal government initially enticed the physicians with subsidizing the cost of implementing such hardware and software requirements (you pay now and we will determine “meaningful use” later and reimburse part of your expense) and then lowered the boom by saying that those that did not implement EMR in their offices would be penalized annually on an incremental basis, starting at a 1.0% reduction in their Medicare reimbursements.

SGR and the “Doc Fix.”

The only thing left to tackle by the bureaucrats was the SGR (Sustained Growth Formula) whereby the physicians were being paid for services rendered through the CMS system. The polity seeing the red climbing the financial charts decided that to keep the costs down, the doctors would have to have a cut in their payments. So new formulas were used and to achieve the required cuts in healthcare costs, a 21%, then a 24.7% and finally a 30% cut had to be made to the physician reimbursement to recast the resources to service the millions of newly added individuals to the healthcare roster. The problem here was that using such draconian measures and using them as the sword of Damocles, forced the physicians to bow out of the Medicare system. After all being a physician is still not considered “indentured servitude.” The policy-makers fearful of a backlash from the voters unable to pull the lever, keep kicking the can forward because they can’t stomach losing their privileged seats in the halls of Congress where entitlements are sprinkled everywhere and everything is for free all admixed with a pension that would make CEOs of a large company blush!

Meanwhile the physicians who had private practices initially employing one or two individuals as office staff suddenly found themselves with 10,11 or even 12 members of the staff each fulfilling some regulatory requirement. The cost of rendering care suddenly seemed insurmountable. They had to find alternatives. Many closed their offices; some turned into entrepreneurs, chefs, businessmen and women while others found shelter in hospitals working as hospitalists.

Hospitalists and Outcomes.

Hospitals, too had to remake their image and those that did not venture into the new grid of such forced compliance, or were serving the indigent and poor patient clientele became victims to the financial losses and closed doors. The nonprofit large institutions and most for-profit hospitals were happy because they controlled the physician behavior through their paycheck and rallied large resources to pay their CEOs and CFOs. Many small hospitals merged with larger ones as promises were made and appointments to storied positions meted out to the acquired administrative staff. The consolidation resulted in a safety for the hospitals as 83% of the newly minted doctors out of residency wanted to be on the hospital payroll and forfeit independence to this new form of subjugated practice of medicine. This number a short four years before was at 18%.

Time forces reality to rear its ugly head eventually; a review of the costs suggested that the cost of rendering patient care by the hospitalists and hospitals had, via this model skyrocketed, actually doubled. The AHA lobby along with the patient advocacy groups continued the pressure on the policy-makers not to cut costs to the hospitals. Meanwhile in the dimly-lit rooms astride the large chambers, future is being planned to reduce the salaries of the physicians and base it on productivity. Some will feel the pinch of a pink slip soon. After all something will have to give and it will be the new, expensive employees. A substitution will be needed. Always ratcheting down payments to the new incoming “eager to change the world” doctors, indoctrinated in the cost-conscious, arbitrary “appropriateness of care.”

Back to the Envisioned Future.

From a global perspective given the limited resource of physician and no plans to increase recruitment of younger minds into the medical field, a band aid is being offered by convincing the laity that other “providers” including nurses, physician assistants, and nurse practitioners could function as ancillary physicians and “better” care would be rendered. The experts cite the European and the United Kingdom models. (In UK, five years ago a bill in the parliament was floated to allow nurses to perform major abdominal surgeries ~ it was defeated by one vote). Alas what they don’t include is the 6-month wait for specialists, an equal wait for surgeries, multiple cancellations of surgeries, lack of new life-extending medicines and a medical staff embedded in the bureaucratic morass unable to lift itself from a recliner to render care to the sick. They, the policy-makers also figured that these “providers” would receive a lower reimbursement because of their education and everyone would be covered. Unfortunately the seams of this fabric seem rather frayed. The hue and cry from the public used to “I want it now” over equity will be loud and clear soon.

So what is the answer to this demand and desire for a "controversial" substitution model as the standard bearer for all healthcare in the land.

Maybe some answers in the next discussion.


References:

UK model of Healthcare under NHS

Patient Harm under NHS

General Practioners complain about patient harm.

Total projected cost of PPACA

PPACA cost and options for Employers

Medicare Law 1965

Bankruptcy in Municipalities across US

EMR Mandate

Medicare Assignments

The Rise in the number of Hospitalists